
Prostate cancer presents a unique clinical challenge, not because it is always immediately life-threatening, but because it often isn’t.
For men with early-stage disease, decisions about when and how to treat are rarely straightforward. Intervening early may offer disease control but can come with lasting effects on urinary and sexual function. Deferring treatment helps preserve those functions but introduces the psychological burden of living with a known cancer.
This tension reframes the clinical question. It is no longer solely about how to treat the disease, but how to guide a patient through a decision that directly impacts his quality of life.
I’ve always prioritized shared decision-making and individualized care, working with my patients to align treatment strategies with their personal goals and values. This means I start by asking each patient a simple but essential question: What is most important to you?
Prostate Cancer Treatments and Trade-offs
More than 3.5 million men in the U.S. are currently living with prostate cancer, and the incidence has risen by roughly 3% annually over the past decade. The good news is that when detected early, prostate cancer is highly treatable and often curable.
At the same time, our gold standard therapies — radical prostatectomy and radiation therapy — come with well-known trade-offs. For some patients, the risks of urinary incontinence and erectile dysfunction raise a red flag, leading them to delay or even avoid treatment altogether.
For years, that left many men with early-stage disease feeling like they were forced to choose between active surveillance or aggressive intervention. The introduction of transrectal high-intensity focused ultrasound about two decades ago offered an alternative but still came with the same two troublesome side effects.
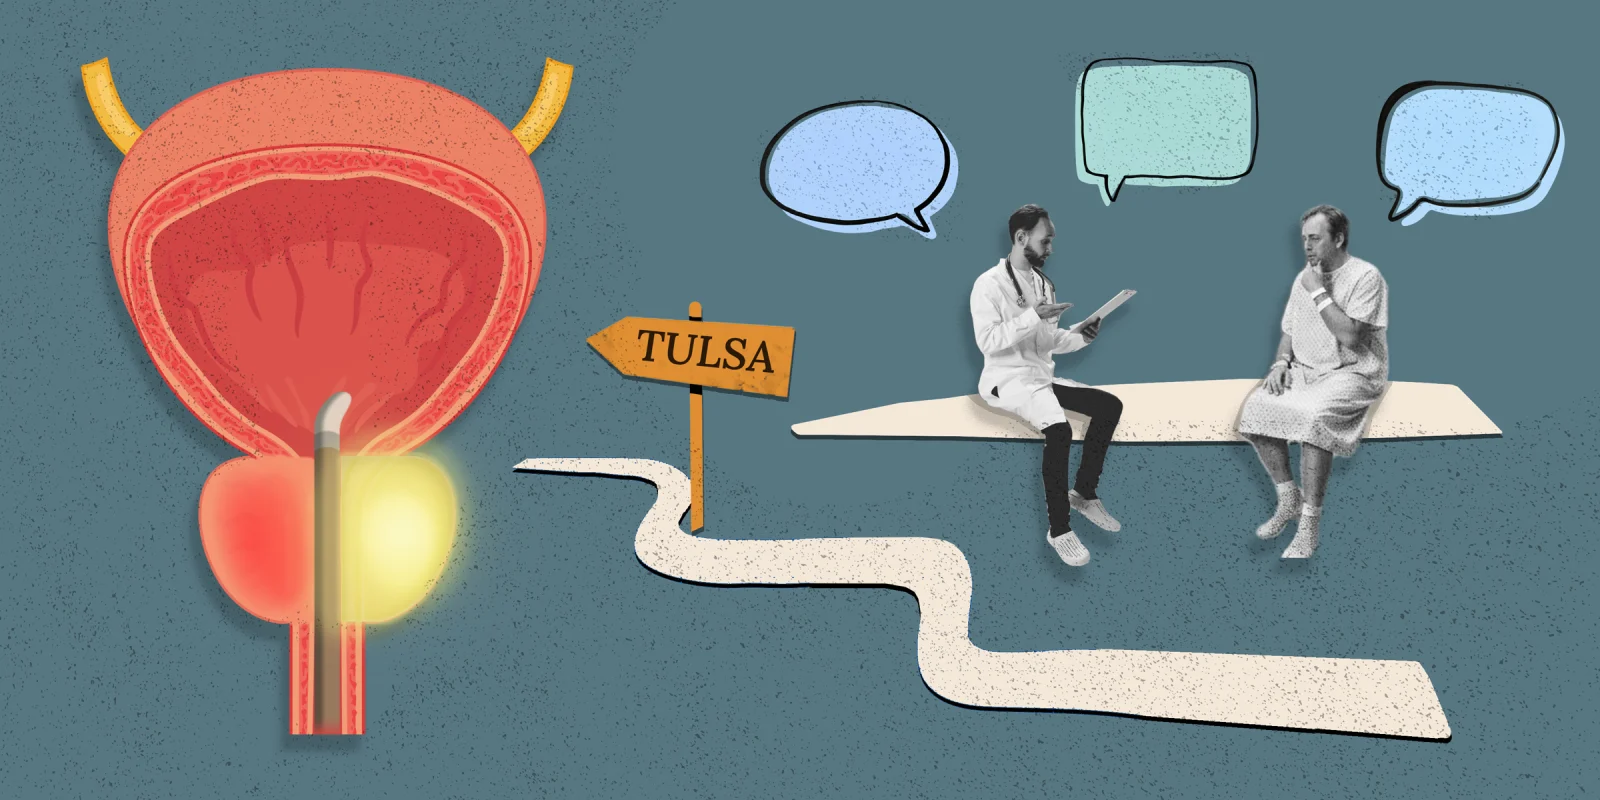
In my practice, addressing that gap has led me to incorporate MRI-guided transurethral ultrasound ablation (TULSA) as an additional option for appropriately selected patients. TULSA offers a minimally invasive, incision-free, radiation-free outpatient treatment for localized prostate cancer and can also be used to treat benign prostatic hyperplasia (BPH). It uses the same technology as high-intensity focal ultrasound but delivers instead through the urethra, which introduces some meaningful safety and control advantages.
A New Application of a Widely Used Technology
The TULSA procedure is performed under real-time MRI guidance with robotic assistance. A catheter-based ultrasound applicator is placed within the urethra, allowing directional energy delivery outward into the prostate.
What I like most is that TULSA offers patients a “middle ground” option between active surveillance and radical treatment. It is another tool in our therapeutic toolbox, allowing us to pursue disease control while also reducing the risk of urinary and sexual side effects that many patients fear most. Importantly, TULSA provides flexibility because we can perform whole-gland or partial prostate tissue ablation, and it does not preclude future treatment with surgery or radiation.
How the TULSA Procedure Works
Performed inside an MRI suite, the TULSA procedure typically takes 2-3 hours under general anesthesia. The transurethral applicator contains multiple therapeutic ultrasound elements that rotate to deliver controlled thermal energy, heating tissue to above 55°C to achieve ablation.
MR thermometry allows us to monitor tissue temperature in real time and adjust treatment as needed. We can actively limit heat exposure to critical structures like the sphincter muscles that manage continence and the neurovascular bundles that protect erectile health. Built-in cooling mechanisms also help protect the urethra and rectal wall.
From a surgeon’s perspective, the ability to make intraoperative adjustments with real-time imaging is a significant strength. The system is highly customizable so we can tailor treatment to the patient's prostate size, shape, and tumor location, whether we’re treating focally or addressing the entire gland.
At the end of the case, we obtain contrast-enhanced MRI imaging to see the non-viable tissue and validate that the treatment was successful. I’ve found that reviewing those images with patients afterward has been a beneficial part of the care experience because they can literally see what was treated.
Treating Residual or Relapsed Disease
Another significant benefit of the TULSA procedure is that it does not preclude future treatment with surgery or radiation. If patients need future prostate treatment, they can have a repeat TULSA procedure or choose any other type of prostate therapy to address their needs. Additionally, TULSA can be performed on patients who have previously had prostatectomy or radiation therapy and are now experiencing relapsed or residual disease, offering a new treatment pathway for patients who otherwise have limited options.
Improving Quality-of-Life Outcomes
Early and mid-term data have been encouraging. The TULSA-PRO Ablation Clinical Trial (TACT) was a prospective, observational multicenter study of patients with localized prostate cancer that demonstrated effective tissue ablation and PSA levels with low rates of toxicity and residual disease:
At one year after receiving the TULSA procedure, median prostate volume decreased by 92%, and 85% were free of Grade Group 2 or higher disease.
At five years, PSA had decreased from 6.3 ng/ml to 0.63 ng/ml. Additionally, 92% recovered pad-free continence and 87% preserved erectile function.
A separate Phase 2 study evaluated TULSA for BPH and found 100% maintained urinary control, 94% preserved erectile function and 96% were able to stop taking BPH medication.
Providing Patient-Centered, Whole-Person Care
There is no perfect procedure for prostate cancer. However, by offering a patient options and education, one of those choices will be as close to perfect as possible for that patient when it comes to meeting their needs and expectations for the future.
Some patients with low-grade prostate disease will choose surgery. Others will prefer radiation. What TULSA adds is another evidence-based option for patients who want treatment but are concerned about quality-of-life trade-offs.
For me, it comes back to making sure patients feel informed, heard, and supported in their decision-making. When a patient leaves my office with a plan in hand that genuinely feels right to them, I know I’ve met them where they are.
The author has no conflicts of interest to disclose.





